Sublocade vs. Vivitrol: How Two Monthly Injections Differ
Both medications are monthly injections given in a clinic. People on Long Island often hear about them together. But they work in opposite ways inside the brain.
Written by Benjamin Zohar, NCACIP · Edited by Ezra Zohar, M.S. Ed. · Published · Updated · Medically reviewed by Brandon McNally, RN on
Quick answer
Sublocade contains buprenorphine, a partial opioid agonist. It gently activates opioid receptors to ease cravings and withdrawal. Vivitrol contains naltrexone, an opioid antagonist. It blocks opioid receptors and has no opioid effect. Vivitrol requires being fully off opioids first, usually 7 to 10 days. Sublocade does not.
- Sublocade = buprenorphine (partial agonist). Vivitrol = naltrexone (antagonist).
- Vivitrol usually requires 7–10 opioid-free days before the first shot.
- Vivitrol is also FDA-approved for alcohol dependence; Sublocade is not.
- Both are given by a healthcare professional, never self-injected.
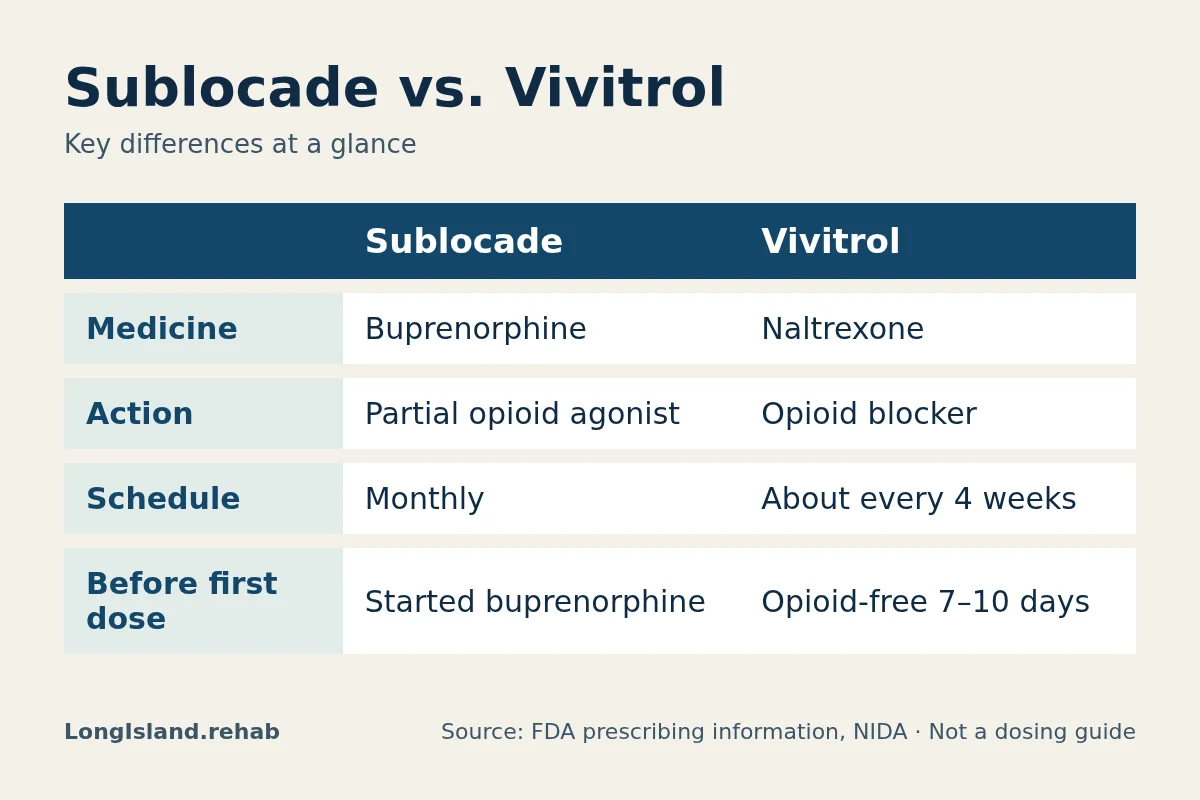
Sublocade vs. Vivitrol at a glance
| Feature | Sublocade | Vivitrol |
|---|---|---|
| Active ingredient | Buprenorphine extended-release | Naltrexone extended-release |
| How it works | Partial opioid agonist | Opioid antagonist (blocker) |
| Injection type | Subcutaneous (under the skin) | Intramuscular (buttock muscle) |
| Schedule | Monthly | About every 4 weeks |
| Before starting | Transmucosal buprenorphine first (single dose or ongoing), per label | Opioid-free period, usually 7–10 days |
| FDA-approved uses | Moderate to severe opioid use disorder | Opioid dependence (after detox) and alcohol dependence |
| Controlled substance | Yes (Schedule III) | No |
Based on current FDA prescribing information. Labels change; your prescriber follows the latest version.
How each medication works
Buprenorphine attaches tightly to opioid receptors but only partly activates them. This can reduce cravings and withdrawal. It also has a "ceiling effect" on breathing suppression, though risk rises when mixed with sedatives or alcohol.
Naltrexone attaches to the same receptors and blocks them. It does not relieve withdrawal. If someone uses opioids while on Vivitrol, the blockade can reduce their effect.
Starting treatment
Vivitrol can cause sudden, severe withdrawal if opioids are still in the body. That is why the label calls for an opioid-free period first. Many people complete medically supervised detox before the first dose.
Sublocade is started after transmucosal buprenorphine. A 2025 FDA label update describes starting after a single dose, as well as in people already on daily buprenorphine. A prescriber decides timing based on the full history.
What research shows
The NIH-funded X:BOT trial compared extended-release naltrexone with daily buprenorphine-naloxone. Once started, both worked similarly. But more people had trouble getting started on naltrexone because of the detox step.
Direct head-to-head trials of Sublocade versus Vivitrol are limited. Choices are usually made on individual factors.
Important safety points
After stopping Vivitrol, or near the end of a dosing cycle, tolerance may be lower. Using opioids at that point carries a higher overdose risk, according to the FDA label.
Sublocade carries a boxed warning. Serious harm or death can occur if it is injected into a vein. That is why it is only given in certified healthcare settings.
Side effects and safety
- Vivitrol given while opioids are still in the body can cause sudden, severe withdrawal. This is the main reason for the opioid-free period.
- After a missed Vivitrol dose or after stopping, tolerance may be lower than before. Opioid use then carries a higher overdose risk (FDA label).
- Sublocade has a boxed warning: serious harm or death can occur if it enters a vein. It is only given by a professional in a certified setting.
- Vivitrol can cause injection-site reactions in the buttock muscle, and the label warns about liver effects. Sublocade can cause constipation, nausea and injection-site lumps.
Questions about switching to ask a clinician
Switching between these medications should only be planned with a prescriber. These questions can help that conversation.
- How long would I need to wait after my last Sublocade injection before naltrexone could be safe?
- Would I need a test or a supervised step before the first Vivitrol shot?
- If I am moving from Vivitrol to buprenorphine, how soon can that start?
- What is my plan for cravings during any gap between medications?
Insurance and access
- Ask whether the office gives both injections or only one. Some programs offer naltrexone but not buprenorphine, or the reverse.
- If you are already opioid-free (for example, after residential care or a hospital stay), ask whether Vivitrol can start before discharge.
- Ask your plan whether either injection needs prior authorization, and whether it is billed under pharmacy or medical benefits.
Finding care on Long Island
Across Nassau and Suffolk counties, office-based buprenorphine prescribers are more common than clinics offering injectables. Methadone for opioid use disorder is only available through certified opioid treatment programs.
- Ask directly: "Do you offer Sublocade and Vivitrol, and do you keep them in stock?"
- First visit: ask what the assessment includes and how soon medication can start.
- Insurance: call the number on your card and ask about prior authorization before the first dose.
- Scheduling: ask how often visits happen in the first month and later.
- Continuity: ask who to call between visits, and what happens if you move or change plans.
New York State lists certified programs through the OASAS provider directory.
Appointment checklist
Bring these to your first visit:
- A list of every medicine and supplement you take, including doses.
- Your recent substance use, including the last time you used opioids.
- Your insurance card and any prior authorization paperwork.
- Questions about the schedule, side effects and what to do if you miss a visit.
- Contact details for any other doctors involved in your care.
Evidence and uncertainty
FDA-approved medications for opioid use disorder are strongly supported by research, according to NIDA. Direct head-to-head trials between specific long-acting products are limited. Choices depend on history, goals, other health conditions and access.
Frequently Asked Questions
Get answers to common questions about our 24/7 crisis helpline and addiction support services.
Still have questions? Our crisis counselors are available 24/7.
Call 844-338-6969Sources and editorial information
- FDA: Sublocade (buprenorphine extended-release) prescribing information
- FDA: Vivitrol (naltrexone extended-release) prescribing information
- Lee JD et al. X:BOT trial, The Lancet (2018) — extended-release naltrexone vs buprenorphine-naloxone
- NIDA: Medications to Treat Opioid Use Disorder research report
- FDA: Information about Medications for Opioid Use Disorder (MOUD)
- NIH StatPearls: Naltrexone
Written by Benjamin Zohar, NCACIP, and edited by Ezra Zohar, M.S. Ed. Medically reviewed by Brandon McNally, RN. See our editorial guidelines.
Medical disclaimer: This article is for education only and is not medical advice. Long Island Rehab Helpline is an independent treatment-navigation resource, not a treatment provider. Talk with a licensed prescriber about your situation.
Questions about medication options?
If you would like help finding licensed providers on Long Island that offer these medications, you can explore MAT options or talk with a treatment navigator at (844) 338-6969.